






Only 1L therapy delivers the longest window of PFS benefit
in HR+/HER2- mBC1-10
Decline in mPFS and deterioration of QoL after disease progression on 1L treatment

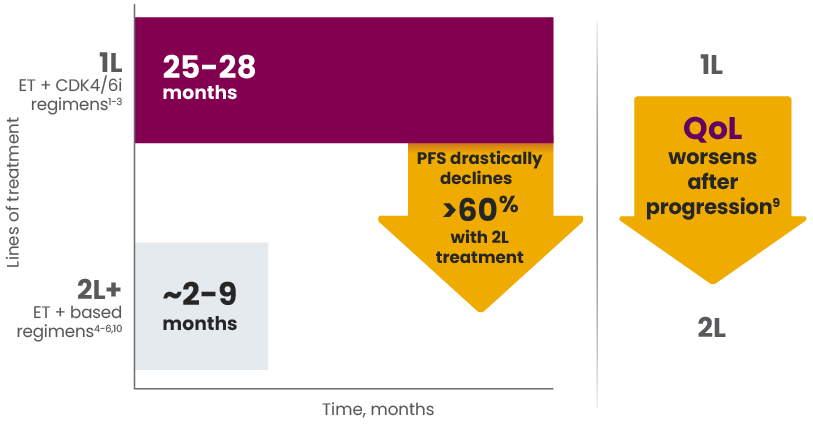
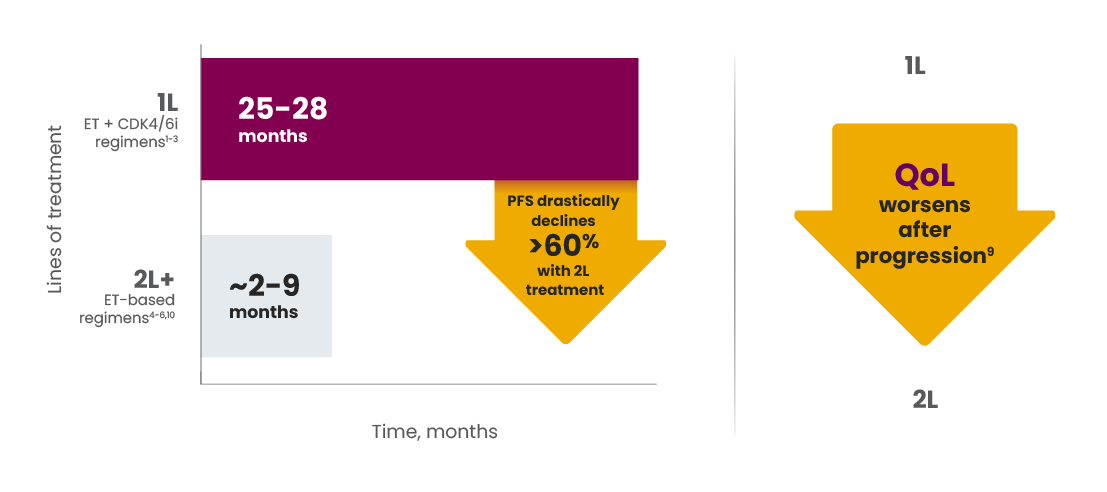
PFS ranges for 1L and 2L were based on phase 2/3
clinical trial data evaluating ET + targeted
therapy regimens.1-10


Patient portrayal
- Works in the office
- Enjoys morning walks with her dog
- Is planning her son’s wedding next year
1L therapy is your best chance to maximize her time without disease progression1-10

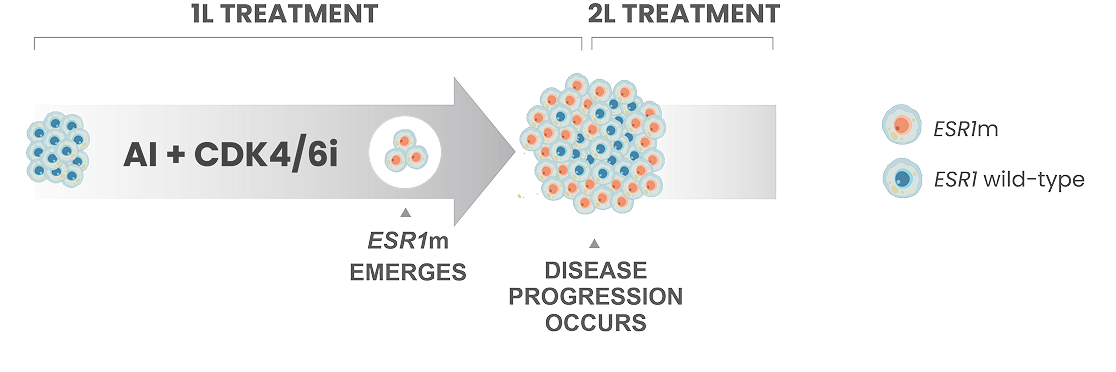
ESR1m can emerge at any time during 1L, signaling the countdown to disease progression11-13
Up to 40% of patients on 1L AI + CDK4/6i develop ESR1m, tripling the risk of disease progression 6 months after emergence11,12
Current 1L approach
Unaddressed endocrine resistance increases tumor genomic complexity, which may be harder to treat in 2L11-15
Next-generation 1L approach
SERENA-6: Designed to proactively address emerging endocrine resistance to extend time on 1L CDK4/6i12,14-17

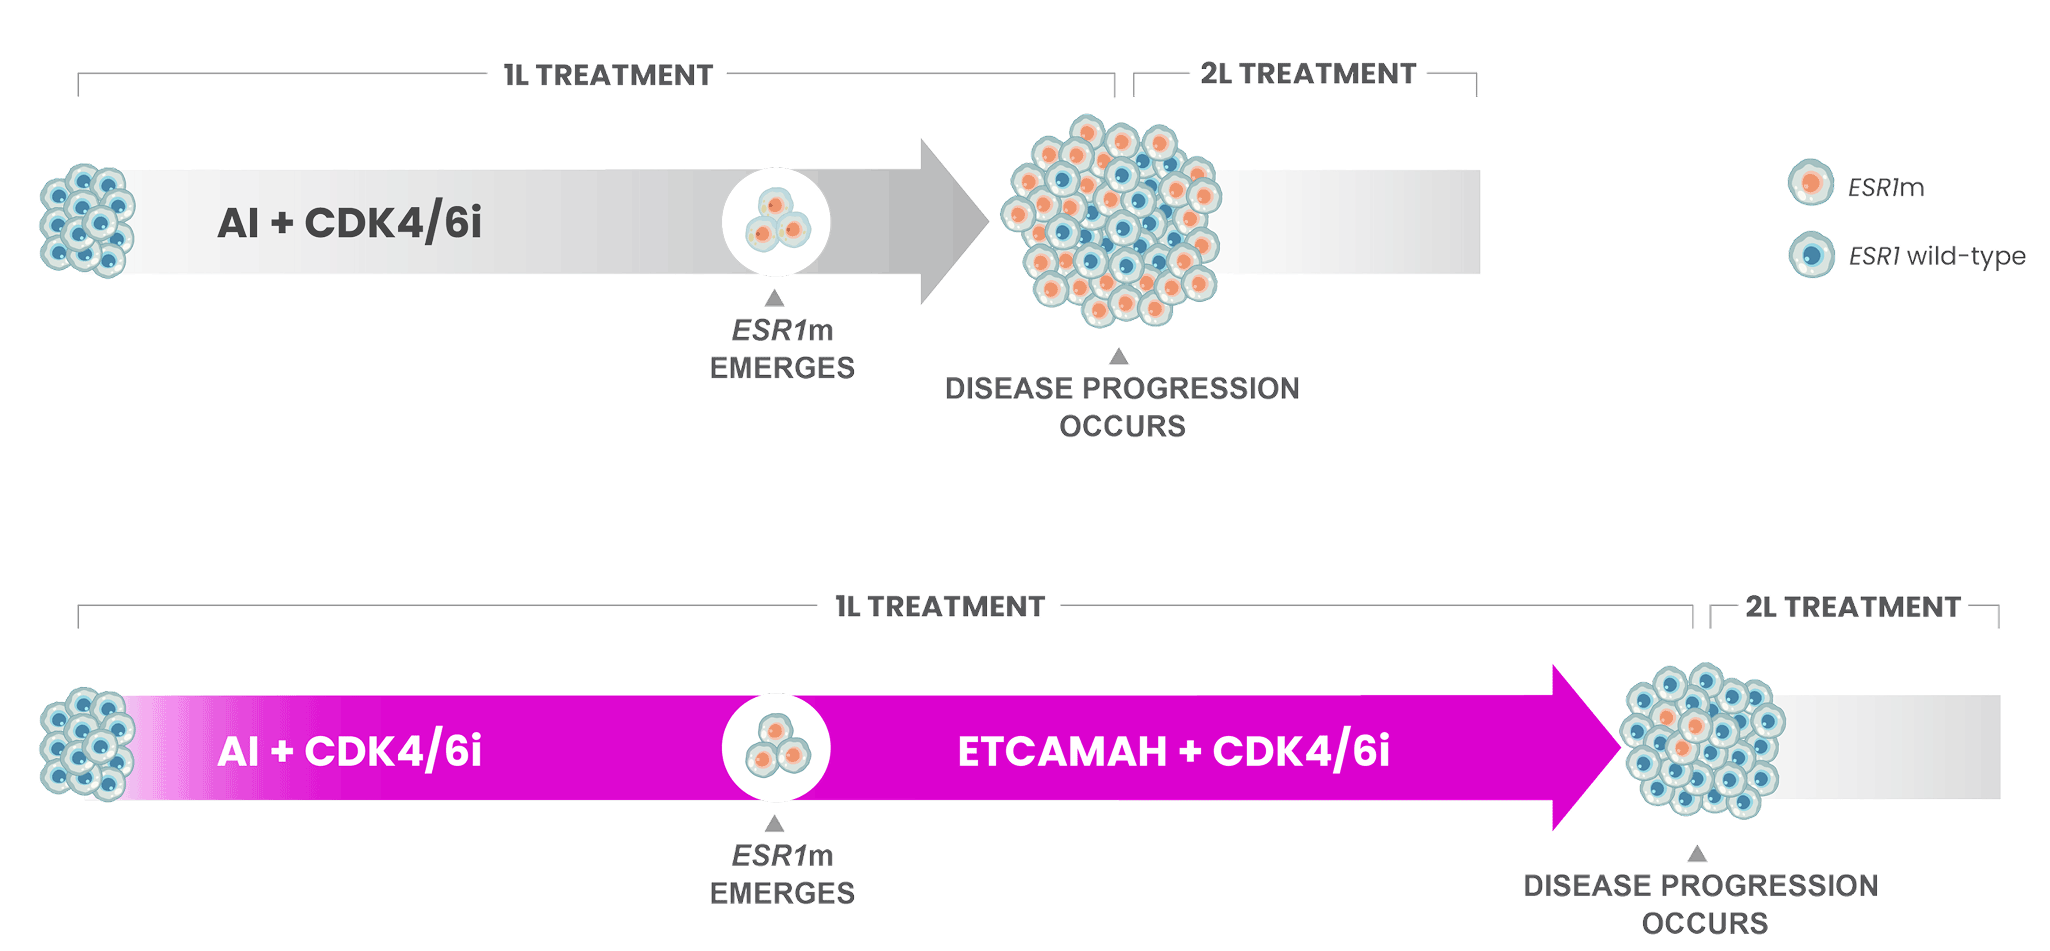

Stay proactive against progression: Intervene upon ESR1m detection for the opportunity to extend PFS on 1L CDK4/6i12
1L=first line; 2L=second line; AI=aromatase inhibitor; CDK4/6i=cyclin-dependent kinase 4/6 inhibitor; ESR1=estrogen receptor 1; ESR1m=estrogen receptor 1 gene mutation; ET=endocrine therapy; HER2-=human epidermal growth factor receptor 2-negative; HR+=hormone receptor–positive; mBC=metastatic breast cancer; mPFS=median progression-free survival; PFS=progression-free survival; QoL=quality of life.
References:
- Finn RS, Martin M, Rugo HS, et al. Palbociclib and letrozole in advanced breast cancer. N Engl J Med. 2016;375(20):1925-1936. doi:10.1056/NEJMoa1607303
- Hortobagyi GN, Stemmer SM, Burris HA, et al. Updated results from MONALEESA-2, a phase III trial of first-line ribociclib plus letrozole versus placebo plus letrozole in hormone receptor-positive, HER2-negative advanced breast cancer. Ann Oncol. 2018;29(7):1541-1547. doi:10.1093/annonc/mdy155
- Johnston S, Martin M, Di Leo A, et al. MONARCH 3 final PFS: a randomized study of abemaciclib as initial therapy for advanced breast cancer. NPJ Breast Cancer. 2019;5:5. doi:10.1038/s41523-018-0097-z
- Kalinsky K, Bianchini G, Hamilton E, et al. Abemaciclib plus fulvestrant in advanced breast cancer after progression on CDK4/6 inhibition: results from the phase III postMONARCH trial. J Clin Oncol. 2025;43(9):1101-1112. doi:10.1200/JCO-24-02086
- Turner NC, Oliveira M, Howell SJ, et al; CAPItello-291 Study Group. Capivasertib in hormone receptor-positive advanced breast cancer. N Engl J Med. 2023;388(22):2058-2070. doi:10.1056/NEJMoa2214131
- Bidard FC, Kaklamani VG, Neven P, et al. Elacestrant (oral selective estrogen receptor degrader) versus standard endocrine therapy for estrogen receptor-positive, human epidermal growth factor receptor 2-negative advanced breast cancer: results from the randomized phase III EMERALD trial. J Clin Oncol. 2022;40(28):3246-3256. doi:10.1200/JCO.22.00338
- Rugo HS, Bardia A, Marmé F, et al. Sacituzumab govitecan in hormone receptor-positive/human epidermal growth factor receptor 2-negative metastatic breast cancer. J Clin Oncol. 2022;40(29):3365-3376. doi:10.1200/JCO.22.01002
- O’Shaughnessy J, Schwartzberg L, Piccart M, et al. Results from CONTESSA: a phase 3 study of tesetaxel plus a reduced dose of capecitabine versus capecitabine alone in patients with HER2-, hormone receptor + (HR+) metastatic breast cancer (MBC) who have previously received a taxane. Presented at: San Antonio Breast Cancer Symposium; December 8-11, 2020; San Antonio, TX. Presentation GS4-01.
- Marschner N, Zacharias S, Lordick F, et al. Association of disease progression with health-related quality of life among adults with breast, lung, pancreatic, and colorectal cancer. JAMA Netw Open. 2020;3(3):e200643. doi:10.1001/jamanetworkopen.2020.0643
- Jhaveri KL, Neven P, Casalnuovo ML, et al; EMBER-3 Study Group. Imlunestrant with or without abemaciclib in advanced breast cancer. N Engl J Med. 2025;392(12):1189-1202. doi:10.1056/NEJMoa2410858
- Clatot F, Perdrix A, Beaussire L, et al. Risk of early progression according to circulating ESR1 mutation, CA-15.3 and cfDNA increases under first-line anti-aromatase treatment in metastatic breast cancer. Breast Cancer Res. 2020;22(1):56. doi:10.1186/s13058-020-01290-x
- Bidard FC, Mayer EL, Park YH, et al; SERENA-6 Study Group. First-line camizestrant for emerging ESR1-mutated advanced breast cancer. N Engl J Med. 2025;393(6):569-580. doi:10.1056/NEJMoa2502929
- Grinshpun A, Chen V, Sandusky ZM, Fanning SW, Jeselsohn R. ESR1 activating mutations: from structure to clinical application. Biochim Biophys Acta Rev Cancer. 2023;1878(1):188830. doi:10.1016/j.bbcan.2022.188830
- Cabel L, Bachelot T, Hardy-Bessard AC, et al. 1O Kinetics and determinants of blood ESR1 mutation under AI and palbociclib in HR+/HER2- metastatic breast cancer patients in the PADA-1 trial. Presented at: ESMO Breast Cancer Annual Congress; May 14-17, 2025; Munich, Germany.
- Pejerrey SM, Dustin D, Kim JA, Gu G, Rechoum Y, Fuqua SAW. The impact of ESR1 mutations on the treatment of metastatic breast cancer. Horm Cancer. 2018;9(4):215-228. doi:10.1007/s12672-017-0306-5
- Oliveira M, Hamilton EP, Kulyaba Y, et al. Dynamics of ESR1 mutation (ESR1m) circulating tumour DNA (ctDNA) in patients (pts) with estrogen receptor (ER)+ HER2- metastatic breast cancer (mBC) receiving camizestrant or fulvestrant: exploratory analyses from the SERENA-2 trial. Abstract presented at: ESMO Congress; September 13-17, 2024; Barcelona, Spain.
- Data on File. US-112875. AstraZeneca Pharmaceuticals LP, 2026.


 For US healthcare professionals

